Left Bundle-Branch Pacing versus Right Ventricular Pacing for Atrioventricular Block.
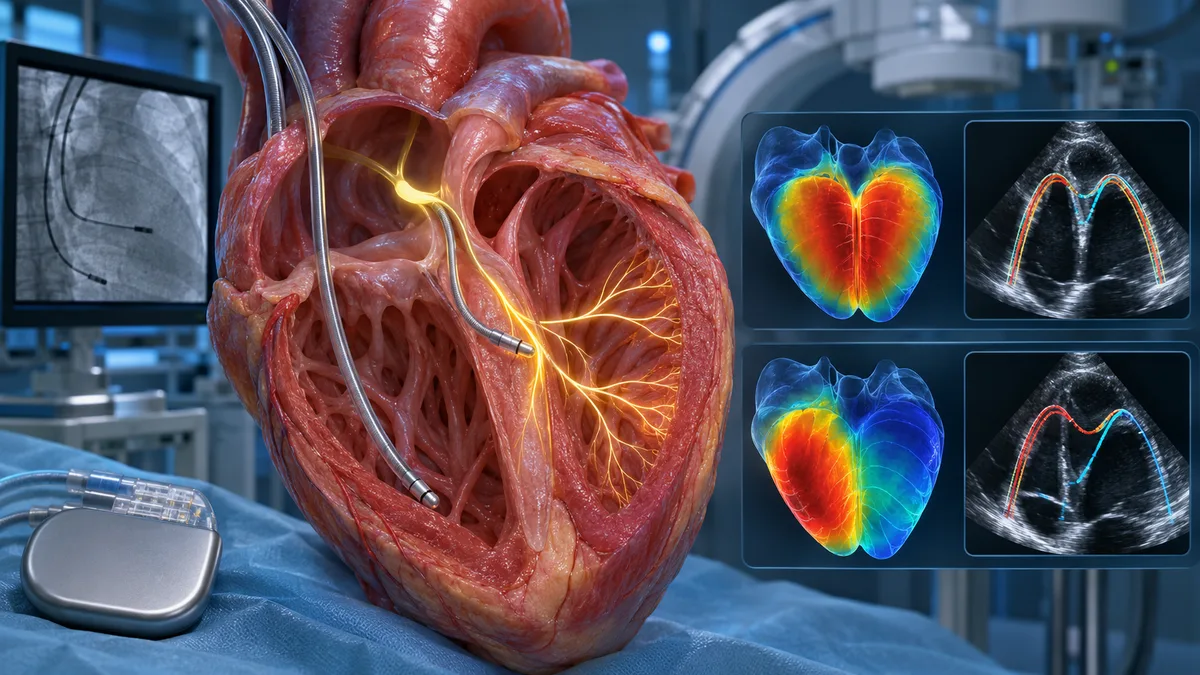
Right ventricular pacing is associated with cardiac dyssynchrony and left ventricular systolic dysfunction. Left bundle-branch pacing preserves left ventricular electrical and mechanical synchrony, but its clinical benefits relative to right ventricular pacing in patients with atrioventricular block remain unclear. In this investigator-initiated, international, open-label, randomized, controlled trial, we assigned patients with atrioventricular block in a 1:1 ratio to receive left bundle-branch
Right ventricular pacing is associated with cardiac dyssynchrony and left ventricular systolic dysfunction. Left bundle-branch pacing preserves left ventricular electrical and mechanical synchrony, but its clinical benefits relative to right ventricular pacing in patients with atrioventricular block remain unclear. In this investigator-initiated, international, open-label, randomized, controlled trial, we assigned patients with atrioventricular block in a 1:1 ratio to receive left bundle-branch pacing or right ventricular pacing. The primary outcome was a composite of death from any cause, hospitalization for heart failure, or pacing-induced cardiomyopathy. A total of 702 patients underwent randomization, with 348 assigned to receive left bundle-branch pacing and 354 to receive right ventricular pacing; 17 patients (6 in the left bundle-branch pacing group and 11 in the right ventricular pacing group) were excluded before device implantation. A total of 685 patients (342 in the left bundle-branch pacing group and 343 in the right ventricular pacing group) were included in the modified intention-to-treat analysis. The mean age of the patients was 68.4 years, and 57.5% were men. At the prespecified interim analysis, the data monitoring committee recommended early termination of the trial. At a median follow-up of 35.1 months (interquartile range, 23.6 to 40.7), a primary-outcome event had occurred in 16 patients in the left bundle-branch pacing group and in 35 patients in the right ventricular pacing group (Kaplan-Meier 4-year cumulative incidence, 8.5% and 19.2%, respectively; hazard ratio, 0.41; 95% confidence interval, 0.23 to 0.75; P = 0.003 by a stratified log-rank test). Serious adverse events unrelated to implantation procedures occurred in 39 patients (11.8%) who had received left bundle-branch pacing and in 33 patients (9.3%) who had received right ventricular pacing (P = 0.32). Among patients with atrioventricular block, left bundle-branch pacing was superior to right ventricular pacing in reducing the risk of a composite of death from any cause, hospitalization for heart failure, or pacing-induced cardiomyopathy. (Funded by Project on New Technology of Jiangsu Province and others; OptimPacing ClinicalTrials.gov number, NCT04624763.).